
Elevate Implant Outcomes With the Right Implant Motor
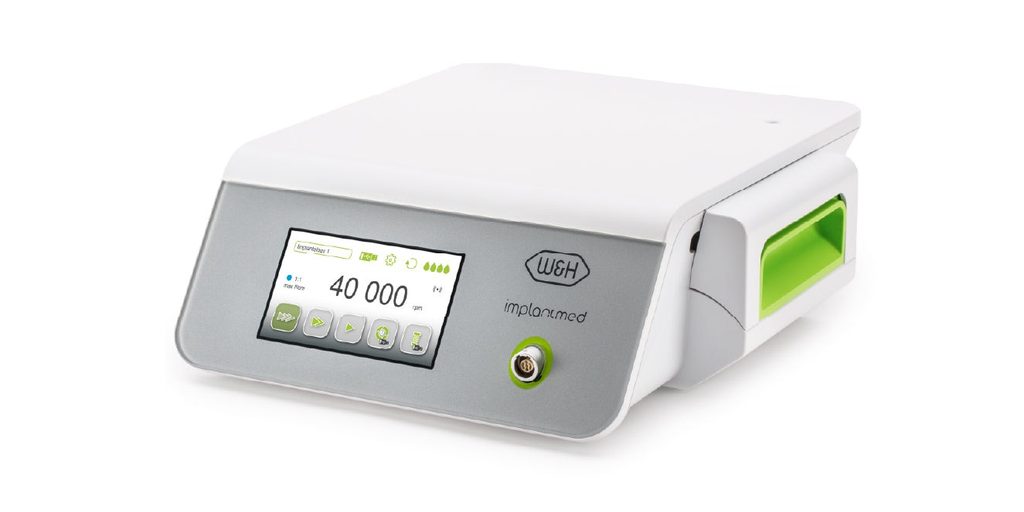
Implant success rates published in the literature routinely exceed ninety-five percent, but those numbers hide a wide practice-to-practice spread. Two clinicians using identical fixtures and identical protocols can produce noticeably different long-term outcomes, and one of the quiet reasons is the electric motor that drives every step from initial pilot drilling to final placement torque. When the motor is under-specified or inconsistent, the operator compensates without realizing it, and small compensations accumulate into wider osteotomies, marginal thermal insult, and inconsistent primary stability. Choosing the right motor is not a luxury upgrade; it is a leverage point that raises the ceiling on what the surgical protocol can achieve. This article explains how motor performance connects directly to clinical results, which technical capabilities matter most, and how to structure a workflow that turns a good motor into predictable outcomes across your case load.
The Direct Link Between Motor Performance and Outcomes
Implant placement depends on precise mechanical control at three moments: initial cortical engagement of the pilot drill, sequential enlargement of the osteotomy, and final seating of the fixture at the target insertion torque. Each of these moments has a narrow window of correct behavior. Too much torque during drilling generates heat; too little torque during placement leaves the fixture under-seated. A dependable implant motor holds its rated speed under load, transitions smoothly between torque settings, and communicates real-time feedback that lets the surgeon feel the bone density rather than guess it. That feedback loop is where clinical judgment meets machine capability.
Speed stability under variable load is perhaps the most underrated specification. A motor that drops speed noticeably when it encounters cortical bone forces the surgeon to increase downward pressure to maintain progress, and that pressure is the primary driver of thermal osteonecrosis. Conversely, a motor that maintains its programmed speed regardless of bone density lets the surgeon rely on the motor for cutting power and focus attention on angle and depth. The difference shows up not on the first case but on the twentieth, when the cumulative effect of steady versus wavering RPM appears in radiographic bone remodeling patterns around the fixtures.
Core Capabilities That Elevate Results
A capable implant motor bundles several features that individually seem minor but collectively define its clinical value. Programmable torque profiles allow the clinician to preset different values for pilot drilling, intermediate osteotomy, tapping, and final insertion, so no reconfiguration is required mid-case. Reverse rotation is essential for tap release and for retrieving stuck drills. An integrated peristaltic irrigation pump synchronized with the drilling program ensures that coolant flow starts and stops with rotation. Foot control granularity, ideally with proportional response rather than on-off behavior, gives the surgeon fine-grained authority over the cutting speed at delicate moments such as breakthrough into cortical bone at the apical extent of the osteotomy.
Torque Control and Speed Ranges
The torque range should extend from very low values, typically around ten Newton-centimeters, up to at least seventy-five or eighty Newton-centimeters, to accommodate both delicate insertion and dense mandibular placement scenarios. Precision at the low end matters more than the peak number, because under-torquing at final seating is what causes fixtures to remain slightly proud. Equally, the speed range must cover the low RPM required for tapping and final placement as well as the higher speed used for pilot drilling. A motor that struggles at very low RPM will hunt and oscillate, which is unacceptable during the final degrees of fixture engagement where feel is everything. Practices that plan to use guided surgery workflows should also verify that the motor supports the specific handpiece contra-angle ratios required by their guide system, since a mismatch invalidates the guided depth control.
Beyond the numbers, consider the interface. A clear, glove-friendly display that shows current torque graphically during insertion helps the surgeon confirm that the reading matches the tactile expectation. Audible cues at threshold events add a second confirmation channel that is especially useful when the operator’s visual field is fixed on the osteotomy. Manufacturers such as Plovio design their surgical control units with these small usability details, and clinics that evaluate an implant motor by using it, not by reading its spec sheet, tend to make better long-term decisions.
Building a Reliable Implant Workflow
The motor is one element of an integrated chain that includes the handpiece, the drill sequence, the irrigation tubing, and the clinical protocol. Elevated outcomes come from aligning all of them. Start by defining the drilling sequence for each implant system used in the practice and program those speeds and torques as named presets on the motor, so the surgeon selects the fixture family rather than reprogramming each parameter. Standardize the irrigation tubing to match the pump, and confirm before each session that the primed flow reaches the handpiece tip. Log the torque values achieved at final insertion for each fixture, because the trend across dozens of cases reveals bone-density patterns that inform future case planning and prosthetic loading decisions. Maintain the motor and its handpiece connectors according to the manufacturer service interval, since delayed maintenance is the most frequent cause of gradual torque drift that goes unnoticed for months.
Training the whole surgical team on the motor’s interface is equally important. Assistants who understand the presets can prepare the correct program before the surgeon steps in, saving several minutes per case and eliminating the small friction of mid-procedure reprogramming. Over dozens of cases, that saved time translates into shorter total appointment length, better patient comfort, and reduced surgeon fatigue on high-volume implant days.
Turning Motor Choice Into Clinical Advantage
The right implant motor does not add to the clinical protocol; it removes friction from it. Steady speed under load, accurate torque throughout the working range, smooth transitions between programmed steps, and a genuinely usable interface together create the conditions where the surgeon’s skill can express itself without mechanical distraction. Once those conditions are in place, small improvements in outcomes compound quickly: cleaner osteotomies produce better primary stability, better primary stability supports predictable healing, and predictable healing raises the practice’s overall success rate over years. Selecting a motor is therefore a strategic decision rather than a purchasing one. Evaluate candidates hands-on, verify torque and speed behavior across the working range, confirm workflow integration with the rest of the surgical chain, and invest in staff training on the interface. When those elements come together, the motor becomes invisible during the case, which is exactly the point, because the clinician can focus entirely on the biology and geometry of a successful implant.